

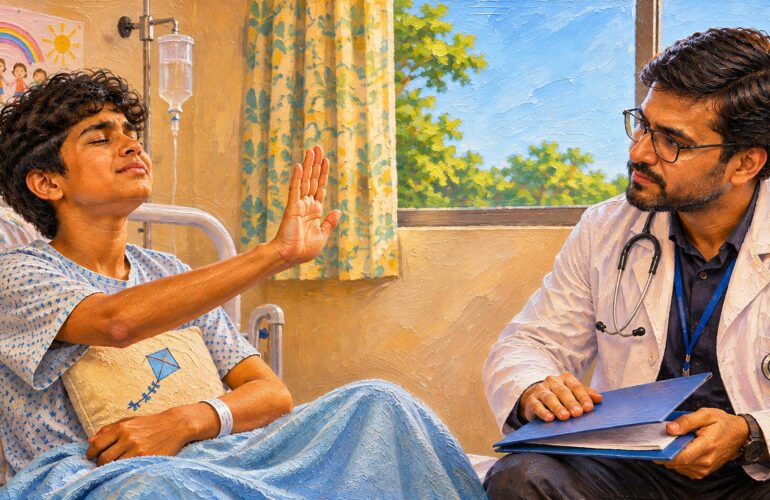
Early in my palliative care training, one principle was repeated so often it became a reflex: be honest. Never lie to a patient, because once you lose their trust, you lose everything. I believed it then, and I largely believe it still. But one boy in his teens made me sit with a harder question. What does honesty mean when a child is telling us, through tears, that he is not ready?
A boy who kept asking
He was living with Ewing’s sarcoma that had spread to his lungs. He wanted to go home, and his family had decided that what mattered most now was time together at home, and we were planning his discharge.
Right up to the day before he left, he kept asking what was happening to him. Not once, but again and again, with growing urgency. Like many parents, his were reluctant for him to know how serious things were.1 Where we work, families often act as guardians of difficult news, and many fear that speaking of death may hasten it.2 We spent time with them, listening to their fears and explaining why we felt their son deserved answers to the questions he was asking. Eventually they agreed that we could talk with him about his prognosis.
It felt like the right thing. We had done what we were taught: we had heard the child, worked patiently with the family and prepared ourselves.
“Please don’t tell me”
I went to his bedside with his paediatric oncologist. Before we had said anything of substance, he began to cry. “Please don’t tell me if there is something bad,” he begged, sobbing.
In that moment, the plan we had worked so hard to agree no longer mattered. What mattered was the child in front of us. I told him we had only come to go over the do’s and don’ts for going home, and that there was nothing wrong with him and he was all good.
He settled almost at once. He went home, and after a few comfortable days with his family, he died peacefully. I will never know what he already understood3,4, or whether he would have asked again.
What he taught me
I have replayed that conversation many times. I said something that was not true, and I do not believe it was a betrayal.
Asking is not the same as being ready. For days he had asked. His family had agreed. We had prepared. Yet at the bedside he showed us his limit, and his limit was the one that counted.
The child’s cues come before our plans. Family permission and good communication skills can open the door. Only the child decides whether to walk through it, and how far.
The question may not be the one we hear. Perhaps his repeated questions were never only a request for facts. Perhaps he also needed to hear that he was safe, that he was going home, and that the people around him were not afraid.
Truth-telling is a process, not a single event. Holding back that day did not mean deciding for him forever.5 It meant letting him choose the pace.
Ask before you tell. Now, before any conversation about prognosis, I ask what the child has noticed and how much they would like to know.1 Some want everything, some want very little, and many change their minds from day to day.
Truth, measured by the good it brings
More than two thousand years ago, the Tamil poet-philosopher Thiruvalluvar wrote in the Thirukkural (Kural 292):
“பொய்மையும் வாய்மை யிடத்த புரைதீர்ந்தநன்மை பயக்கும் எனின்”
“Even falsehood is of the nature of truth if it bringeth forth unmixed good.” (translation by V. V. S. Aiyar)6
For Thiruvalluvar, the worth of our words lies not only in their facts but in the good they bring to the one who hears them.
I still believe in honesty, and I believe many children cope with the truth better than adults fear.3,7 But I no longer believe that honesty means telling every child everything, the moment we are ready to say it.
Sometimes the most honest thing we can do is listen to a child who says, “Please don’t tell me,” and believe him. Then stay.
About the Author:
 Dr. Daniel Raj Joseph Thangasamy is a Pain and Palliative Care Physician at Mahaveer Ashray Hospice, A unit of Cancer Institute (WIA), Sriperumbudur, Tamil Nadu, India. He has been working in palliative care since 2018, with a special interest in paediatric palliative care, communication and improving access to quality palliative care. He holds a National Fellowship in Palliative Medicine and recently completed his MSc in Palliative Medicine for Health Care Professionals at Cardiff University as a Commonwealth Scholar.
Contact: +91 9566997109, dr.j.danny@gmail.com
References
- Ambler J, Brand T, Boucher S. When a child is sick – asking and answering the hard questions. ehospice (International Children’s edition); 1 October 2018. https://ehospice.com/inter_childrens_posts/when-a-child-is-sick-asking-and-answering-the-hard-questions/
- Chaturvedi SK, Loiselle CG, Chandra PS. Communication with relatives and collusion in palliative care: a cross-cultural perspective. Indian J Palliat Care. 2009;15(1):2–9.
- 10 common myths about children’s palliative care. ehospice (International Children’s edition); 14 June 2022. https://ehospice.com/inter_childrens_posts/10-common-myths-about-childrens-palliative-care/
- Bluebond-Langner M. The Private Worlds of Dying Children. Princeton, NJ: Princeton University Press; 1978.
- Taub S, Macauley R; AAP Committee on Bioethics. Responding to parental requests for nondisclosure to patients of diagnostic and prognostic information in the setting of serious disease. Pediatrics. 2023;152(4):e2023063754.
- Thiruvalluvar. The Kural or the Maxims of Tiruvalluvar. Aiyar VVS, translator. Sheramadevi: Bharadvaja Ashrama; 1916.
- Kreicbergs U, Valdimarsdóttir U, Onelöv E, Henter JI, Steineck G. Talking about death with children who have severe malignant disease. N Engl J Med. 2004;351(12):1175–86.


Leave a Reply